
Work With a Doctor Who Really Gets It
Looking for a more individualized approach to your health? Confused about how all the contradictory health advice applies to you? Looking to break free from our failing healthcare model? We have you covered.
Request a medical consult from Dr. Scher today!
Let’s Talk
Send us a message and let us know how we can help you.
Consult With Dr. Scher


The initial consultation is $1,495. Contact Dr. Scher today to see if you qualify.
You can take charge of your health.
Let Dr. Scher show you how.
Let’s Talk
Send us a message and let us know how we can help you.
Meet Dr. Scher, MD
The Low Carb Cardiologist

Hi, I’m Dr. Scher, and I’m changing the direction of preventive cardiology to better serve more people like you with the care you deserve. I’m also the CEO and Lead Physician at Boundless Health and the Low Carb Cardiologist. I spent the past 15 years as a frustrated board-certified cardiologist. My patients weren’t achieving their optimal health, and I didn’t have the time or resources to guide them. That’s why I sought out additional certifications in lipidology, nutrition, personal training, functional medicine, and behavioral change.
It is through this specialized training and working with thousands of patients I recognized how to provide better care. Your health is too important to trust to guidelines designed for the ‘average’ person. You are not average, nor should you want to be!
I’m glad you’re here. It tells me you know you deserve better care. I can’t wait to get started finding your path to true health.
Bret Scher, MD FACC
Board Certified Cardiologist and Lipidologist
Yes, People LOVE Dr. Scher’s Approach

Are you interested in trying a Low Carb-High Fat/Ketogenic lifestyle? If so, great.
Are you looking to your doctor for support in this diet? If so, tread gently.
The medical community has engrained false beliefs that LCHF lifestyle is dangerous to your health. We can blame it on Ancel Keys. We can blame it on an over emphasis on LDL-C. We can blame it on Big Pharma. We can even blame it on the rain! Whatever the reason, you may not get a warm and receptive response from your physician.
But there is hope. Here are my top 6 Tips on How to Talk to Your Doctor About The LCHF/Keto Lifestyle.
1. First, ask for your doctor’s opinion about LCHF
Doctors are people too. How would your spouse react if you said, “I’m no longer taking out the trash/doing the dishes/making dinner. It doesn’t work with my personal philosophy of house chores and we are going to change this. Now.” I hope you have a comfortable couch, cause that’s where you will be sleeping.
Picture instead, “Hi Honey. I was thinking that we may want to reassign some of our house chores to help things get done better and more efficiently without putting too much strain on either of us. What do you think about that? Do you have any thoughts how you would like to change things?” That sounds better, right?
The same approach applies to your doctor. Just don’t start by calling your doctor honey. That’s just awkward. Don’t say, “Hey Doc, I’m going LCHF and need you to order x, y and z blood tests on me now and again in 6 months, and help me get off my meds.” Instead, try a kinder, gentler approach. “Hi Doc. I was thinking of ways to be more proactive about my health. What I have done thus far has not worked as well as I have liked. I have heard a lot about LCHF as a way to lose weight, reduce insulin levels, improve blood glucose control, and feel better. I was thinking of trying it. What do you think about that?” You may not immediately get the answer you want (for instance, I am still taking out the trash every week), but you have opened the lines of communication in a much less confrontational way, which can set you up for success as we discuss other tips below.
2. Measure the effects of Keto on your body with a medical trial
If your doctor is hesitant about you trying LCHF/Keto, suggest a 3- or 6- month trial. Establish what you want to monitor (here’s an eBook I created to help you get started: 10+Medical Tests to Follow on the LCHF Diet). Check what you would like to monitor at baseline and then at the 3-6-month mark. Emphasize you want to experiment to see how your body responds, and that you want his/her expertise in helping analyze the labs to help you progress safely.
Also, if you are on medications for blood pressure, blood sugar or lipids, you will want their guidance with these. Emphasize how you want him or her on your team to help you on your journey and temporary experiment. It is hard to resist when someone genuinely wants your help and thinks you can play a role in their improvement!
3. Show them your results!
Don’t gloat, don’t brag, but make sure you follow up with your doctor and tell them everything you feel and have measured. Do you have more energy? Less stiffness or inflammation? Are your pants fitting looser? And of course, follow up on all the labs to look at the whole picture. You will be surprised how often your doctor will then turn to you and ask you what you have been doing. If they have the time, they will likely say “Tell me more about that.” Yes! This is your opportunity to teach them the power of LCHF/Keto. Then, when the next patient comes around, they won’t be as resistant, and may even start to suggest it themselves. The patient becomes the teacher!
4. Find a doctor who will listen
Our healthcare system is messy. No question. We don’t always have freedom to choose our own doctors. But that doesn’t mean it is impossible to change. Here is a hint: If your doctor isn’t open minded enough to try a self-directed experiment with you, what else are they close minded about? Maybe it is time for a change anyway.
It may not be easy to find a doctor with an open mind who takes your insurance, is geographically desirable, and who is accepting patients, but there are some tricks you can use. Look for a doctor who has been in practice more than seven years, but less than 20 years. In my experience, this is the critical “open minded” window. They have been in practice long enough to be confident in their own skills and are willing to stray from “what everyone else does.” On the other hand, they have not been in practice so long that “That’s the way I have always done it” becomes the reason for their care.
Look for doctors with interests in prevention, sports medicine, or integrative medicine. These suggest more interest in health and less interest in the standard “pill for every ill” medical practice. Lastly, people are developing lists of Keto-friendly doctors online. While these may be small at present, they are growing quickly and hopefully can help you find the right doctor for you.
5. Seek online Keto support
Numerous online sites exist to help you with you transition to a LCHF lifestyle. I have built my blog and Low Carb Cardiologist Podcast to provide information and support on those who are embarking on their healthy lifestyle journeys, with a lot of information about Keto and LCHF.
Some other sites I recommend are DietDoctor.com, 2KetoDudes podcast, and Ketovangelist podcast, to name a few.
6. Take control of your own healthcare journey
As nice as it is to have your physician on board with your health decisions, it is not always needed. As Brian Williamson from Ketovangelist said to me on his podcast, “If your doctor is more interested in your health than you are, then you are in trouble!” I agree with that sentiment, and I encourage everyone to be the driver in their own healthcare. You can still choose to try the LCHF lifestyle even without your doctor. Look for a reputable second opinion doc who is willing to help open lines of communication between you and your doc. That is one of the services I enjoy providing the most. Since I speak the same language, I can usually help someone start the conversation with their doctor.
In addition, online sites such as WellnessFx.com allow you to get your blood drawn and seek consultations with health care providers (Disclaimer: I am one of those providers and get paid for my services. Another disclaimer: I love doing it). If you go this route, I encourage you to then bring your results back to your doctor (See number 3 above). You can now become the teacher, young Jedi.
There you go. With these six simple tips and resources, you will be well on your way to safely adopting a Keto lifestyle. Doctors are people too. Just like everyone else, we like to be needed, we like to be helpful, and we don’t like being told what to do. I just need to remember that the next time my wife “needs” me to clean the toilet….
Thanks for reading.
Bret Scher, MD FACC
Founder, Boundless Health
In the fall of 2018, I was diagnosed with Type 2 Diabetes. I was educated enough to know that there was something I could do about it and set out to change the path I was on by adopting a low carbohydrate/Ketogenic Diet to control my blood sugars. Fortunately, it worked right away- but soon after I discovered that I had some red flags on my cholesterol test results. There is a history of Cardiovascular disease in my family and I was disappointed that I might have to yet again make diet changes but was willing to do what was best for my whole health. After an appointment with a local Cardiologist, I felt somewhat confused about how to move forward. I wanted more information and not just a prescription.
I contacted Dr. Scher for a consult because I wanted to confer with someone who not only understood my condition but who could also give me the latest and soundest advice on how I might treat it and move forward in the best way for me as an individual- not as a statistic. I needed someone who came from a low carb perspective as well as a medical background. My interaction with him was positive, informative and went a long way to making me feel like I could make informed choices without the black and white thinking of well-meaning physicians. He sees the WHOLE person and not just one aspect of their health. Wellness is a journey- and having Dr. Scher along the way is a great way to make the trip!
Lisa K.

Can we be certain that elevated LDL (Low-density lipoprotein) particles have no meaning and can be completely ignored?
Certainly not.
Can we be certain that all LDL particles are deadly and need to be treated to microscopically low levels?
Certainly not.
So, what do we do?
I have seen countless second opinion consults and enrolled numerous clients in my Boundless Health Program who have this exact question. What’s the deal with LDL? Do we worry or don’t we?
Life is much easier when it is black and white, good and bad. I, however, believe in looking for the nuance and trying to understand things a little deeper.
But first, let’s back up a little.
What is LDL and LDL-P?
Cholesterol can be a complex topic that we frequently oversimplify, which I am about to do. In brief, LDL is known as the “bad” cholesterol, the cholesterol that is found in plaque buildup in our hearts. But the truth is that LDL is not inherently bad. In fact, LDL has a purpose in our bodies as part of our immune response and as a fuel and vitamin delivery mechanism to name a few. If vascular injury and inflammation are present, then modified LDL may invade vessel walls and participate in a cascade of events leading to plaque buildup and an eventual heart attack.
LDL-C is a measure of the total amount of cholesterol in our LDL lipoproteins. LDL-P is the total number of the LDL lipoproteins. Studies show that LDL-P is a much better marker for CVD risk than LDL-C. As an analogy, the number of cars on the road matter more than the number of people in the cars.
What are the risks of LDL-P?
On the one hand, trials in the general population show that elevated LDL-P is a risk factor for cardiovascular disease (CVD). This includes a combination of observational trials, genetic mutation trials (mendelian randomization), and drug treatment trials.
All things being equal, based on these trials alone, we should want our LDL-P to be low.
But does LDL alone cause heart attacks and death? Or are there other factors involved?
Of course there are other factors involved in CVD. Vascular injury and inflammation being the two most prominent factors.
Can lowering our LDL-P have risks greater than the potential benefits for certain populations?
Absolutely. Since primary prevention statin trials show we have to treat over 200 people for five years to prevent one heart attack with no difference in mortality, it seems reasonable that certain populations will experience more potential risk than reward.
The Low Carb High Fat Reality
How many LDL or statin trials have specifically looked at individuals on a healthy, real foods, LCHF diet?
None. Not a single one.
How many LDL or statin studies have looked specifically at red headed, left handed boys born the second week of March?
None, at least to the best of my knowledge.
This seems glib but bear with me.
Is there any reason to think a red headed, left handed boy born the second week of March would behave any differently than everyone else in these LDL studies? Not really. Especially if they are eating a standard American diet or a low -fat diet as was almost exclusively studied in every cholesterol or statin trial.
Here’s the more important question. Is there reason to believe individuals on a healthy, real foods, LCHF diet would behave any differently than everyone else in the decades of lipid and statin studies?
There absolutely is reason to believe they may behave differently. There is not clear proof, but there is plenty of reason to suspect it.
Think about the benefits of a LCHF lifestyle.
- Lowers inflammation
- Reverses insulin resistance
- Naturally raises HDL and lowers TG
- Converts majority of LDL particles to larger, more buoyant particles
- Lowers blood pressure
- Reduces visceral adiposity
Could these create an environment where an elevated LDL is less of a concern?
It sure could.
To be clear, I openly acknowledge that we do not have definitive proof that we should have no concern with LDL in this situation. In my opinion, this is a specific scenario that the existing trials simply do not address one way or the other.
So, it seems we have two choices.
- Since we don’t have any proof we can ignore LDL in this setting, we plug the numbers into the 10-year ASCVD calculator and start a statin if the risk is above 7.5%, or we ask the individual to change their lifestyle in hopes the LDL will come down.
- If the individual is enjoying multiple health benefits from their lifestyle, and they are rightly concerned about the potential risks of statin therapy, then we can follow them for any sign of vascular injury or plaque formation, or any worsening of their inflammatory markers or insulin sensitivity. In the absence of any potentially deleterious changes, we can reason that the risk is low, and the benefits of living the healthy lifestyle may outweigh the risks.
The “problem” is that the second option requires a detailed discussion of the risks and benefits. It requires close monitoring and follow up. It requires us to think outside general guidelines and consider everyone as an individual with their own unique circumstance. These are qualities that our current healthcare system sorely lacks. Yet that is the exact care that each individual deserves.
What do we do in the meantime?
I hope someday soon we will have definitive long-term evidence that a high number of large buoyant LDL particles along with elevated HDL, low TG and low inflammatory markers is perfectly safe.
Until that day, we will have to continue to talk to our patients. To see them as individuals. To weigh the lifestyle benefits with the possible risks. That includes seeing the risks in real numbers- not quoting a 30% benefit with statin therapy. Instead, having a real discussion that statins may reduce your risk a heart attack by 0.6% with an increased risk of muscle aches, an increased risk of diabetes, and a potential increased risk for cognitive and neurological dysfunction.
And we will have to understand that the answer won’t be the same for each person. And we can be OK with that.
So, do you have to worry about your LDL? I don’t know. But I welcome the opportunity to explore the question and reach the best answer for you.
Do you have questions about what your lipids may mean for you? What they mean when taken in the context of your lifestyle and overall health picture? If so, you may want to learn more about my Health Coaching Consult.
Thanks for reading,
Bret Scher, MD FACC
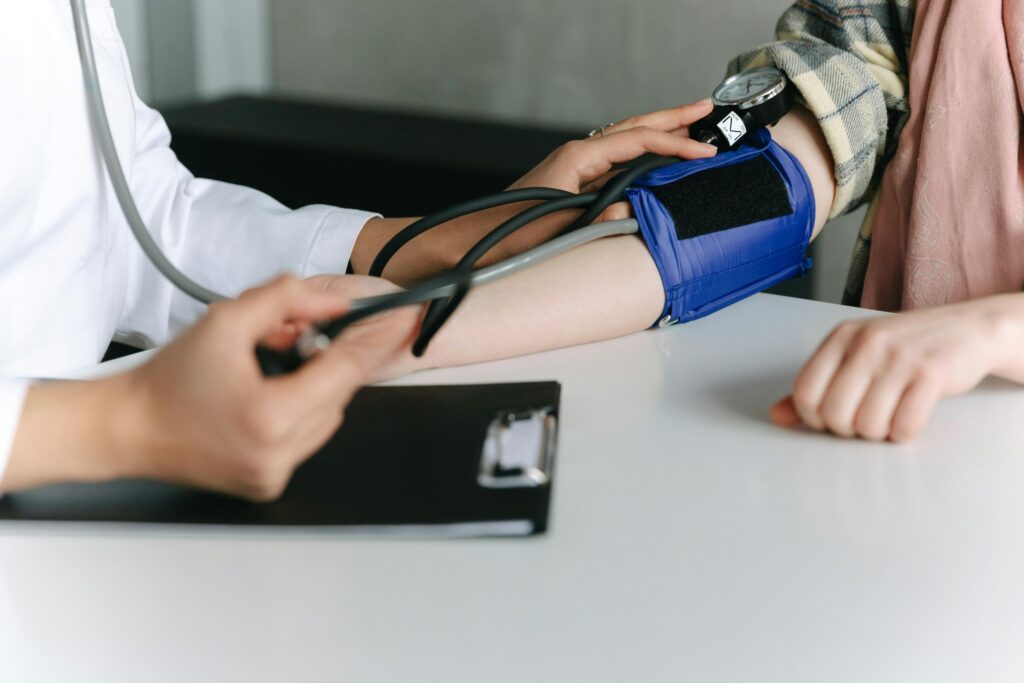
Did you know changing the way you eat may be able to normalize your blood pressure completely? For many people it’s true. But what’s surprising is that it isn’t changing to the diet that most doctors and dieticians recommend.
The DASH diet, Dietary Approach to Stop Hypertension, has long been the “go-to” diet for reducing blood pressure. The DASH diet is a high carbohydrate, low fat diet that recommendseating plenty of fruits, veggies, whole grains, and limiting salt and saturated fat. And while that works for some people, many others can normalize their blood pressure with a nearly opposite approach.
A 2023 study published in The Annals of Family Medicine, demonstrated that a very low carbohydrate diet with no limitations on the amount of salt or the amount or type of fat eaten was better at lowering blood pressure compared to the DASH diet.
Many wonder how this could be, but the answer is pretty straightforward.
Poor metabolic health, from insulin resistance to type 2 diabetes, is a leading cause of high blood pressure. And low carb diets are one of the best lifestyle approaches for improving or even normalizing metabolic health. Therefore, it makes complete sense that a low carb diet would be highly effective at normalizing blood pressure.
Of course there are many other ways to improve blood pressure, such as quitting drugs, tobacco and alcohol, getting regular exercise, managing stress, etc. And these are very important. But since everyone has to eat, it is powerful to eat in a way that can normalize blood pressure.
Let’s explore four ways how low carb diets can help blood pressure.
1- Weight loss
Having overweight or obesity is a strong contributing factor to high blood pressure. And while low-carb eating isn’t the only way to lose weight, it tends to be as good as or even better than low fat eating for weight loss. Some publications even demonstrate weight loss on par with highly effective GLP1 weight loss drugs like Ozemipic and Wegovy.
2- improved metabolic health
As mentioned, metabolic dysfunction is a clear trigger for elevated blood pressure. And while low carb eating isn’t the only way to improve metabolic health, it is likely the most effective dietary pattern for improving metabolic health, and can even do so with or without weight loss.
3- Ketosis
If someone lowers their carbohydrate intake enough, they can enter a state of ketosis, a normal physiologic state where we burn primarily fat for energy instead of carbohydrates. When this occurs, our insulin levels drop to a normal level and we have a natural diuresis, meaning we eliminate sodium and water more than usual. This can help lower blood pressure above and beyond weight loss.
4- Avoiding processed foods
Most well formulated low carb diets avoid highly processed junk foods like potato chips, candy, doughnuts, etc. that can lead to high blood pressure. So, simply eliminating these foods can also contribute to lower blood pressure.
What about salt?
One of the big misconceptions about blood pressure is that we all need to lower our salt intake for better blood pressure. However, this appears to be a gross over-generalization. There’s a growing understanding that a minority of individuals have “salt sensitive” hypertension. This means that the majority are unlikely to affect their blood pressure by altering their salt intake.
Furthermore, where we get our salt likely makes a difference. For insurance, if someone is getting their salt from highly processed foods like chips, pretzels, etc, they are hit with an ultra-processed combination of salt, calories, carbs, and sugars that is bound to raise blood pressure.
But what if someone is eating whole foods like broccoli, cauliflower, steak, and avocado, and they add salt to that meal? Clinical experience suggests our bodies react much differently to this type of salt exposure, and people can dramatically lower their blood pressure despite adding salt to their diet.
Low Carb Eating Works
So while it may not be the right approach for everyone, it is increasingly clear that eating a well-formulated low carb diet is a safe and effective way to lower blood pressure. It’s time to include low carb diets as a first line treatment option for normalizing blood pressure.
Thanks for reading!
Bret Scher MD FACC
I live in McAllen, Texas, where it’s difficult to find a doctor who’s knowledgeable on the benefits of a low-carb lifestyle. Because I battle a high A1C AND high cholesterol, I reached out to Dr. Scher for a consultation to monitor my blood work and develop a plan that will keep my heart healthy and my A1C in check. Before our video-consultation, he responded personally to every question I had via email. When I first reached out, I figured it would take at least a month or more to schedule our consultation, but to my surprise, it was planned just over a week from my initial email!
I like Dr. Scher’s commonsense approach to a healthy lifestyle. He came up with a very-easy-to-follow plan and agreed to review my bloodwork every 6-8 weeks to make sure I’m on the right track. Because of my family’s history, it’s comforting to know I have a cardiologist monitoring my health so that I can prevent a significant problem down the road.
Nicole Southwell
START A CONVERSATION
Connect with Dr. Scher to see if you qualify for the consultation.
Let’s Talk
Send us a message and let us know how we can help you.