
We’re Changing the Cardiology Experience
Because You Deserve Better Care.
The practice of medicine, especially preventive cardiology, is failing patients because it focuses on general guidelines based mostly on numbers: “What’s your LDL?”, “What’s your BMI?” And that’s usually where it stops. It’s dangerous because it focuses on an equation instead of the individual. You are not your numbers. Your body is unique and deserves to be treated as such. We need a transformative shift in cardiology and preventive health care that considers you as an individual.
Let’s Talk
Send us a message and let us know how we can help you.
Introducing
Concierge Preventive Cardiology
with Dr. Scher
What if you could combine…
Now with Dr. Scher’s Concierge Preventative Cardiology, you can!
WELCOME TO
BOUNDLESS HEALTH WITH DR. SCHER
a revolutionary approach to optimizing your health and life!


Find out if this works for you
Connect with Dr. Scher today to see if this model is right for you.
Let’s Talk
Send us a message and let us know how we can help you.
Meet Dr. Scher, MD
CREATOR OF CONCIERGE PREVENTIVE CARDIOLOGY

Hi, I’m Dr. Bret Scher, and I’m changing the direction of preventive cardiology to better you with the care you deserve. I’m also the CEO and Lead Physician at Boundless Health and the Low Carb Cardiologist. I spent the past 15 years as a frustrated cardiologist. My patients weren’t achieving their optimal health, and I didn’t have the time or resources to guide them. That’s why I am revolutionizing my practice of medicine, and why I sought out additional certifications in lipidology, nutrition, personal training, functional medicine, and behavioral change.
It is through this specialized training and working with thousands of patients I recognized how to provide better care. Your health is too important to trust to guidelines designed for the ‘average’ person. You are not average, nor should you want to be!
I also recognize the need for better access and convenience. That’s the heartbeat behind Concierge Preventive Cardiology: open access so together, we can evaluate every facet of who you are and how you can best achieve your goals.
I’m glad you’re here. It tells me you know you deserve better care. I can’t wait to get started finding your path to true health.
Bret Scher, MD FACC
Board Certified Cardiologist and Lipidologist
Yes, People LOVE Dr. Scher’s Approach

Is the Keto Diet Heart Healthy? 7 Reasons Why This Cardiologist Agrees
I am a board certified, card-carrying cardiologist, and I want my clients to eat more fat, more meat, more cheese, more eggs, more avocado, more, more, more.
For decades medical establishments have convinced us to eat low fat, higher carb diets. How has that worked for our health? Here’s a hint, we have record numbers of obesity, diabetes and dementia. Yet, as a cardiologist, that’s the party line I am supposed to support.
But I can’t. It’s just wrong, and I can’t support that line of thinking, not for a second.
Instead, I am a Low Carb Cardiologist. Here are the top Seven reasons why
- Reducing Insulin is Essential to Health and Weight Loss.
Insulin is a hormone naturally secreted by the pancreas to help regulate blood sugar levels. Everything we eat (except possibly for 100% fat meals) causes insulin to rise. That is normal physiology. The problem occurs when our bodies become resistant to the effects of insulin, thus requiring our pancreas to make more and more and more insulin.The problem? Insulin promotes fat storage, increase inflammation and oxidation, and can even help fuel the growth of cancer cells. Therefore, the healthiest approach is one which reduced the level of insulin to the lowest possible levels. As it happens, a Low-carb High-fat or ketogenic lifestyle (LCHF/Keto lifestyle) dramatically improves your body’s sensitivity to insulin, reduces the amount of insulin secreted, and it allows your body to naturally use your fat stores for what they are designed for: Break them down into energy! Once we see that we need to fight chronic elevations of insulin, it becomes obvious why a low-fat diet is harmful, and why a low carb diet is the true path to health. - Eating Fat Improves Your Cholesterol!
Wait, what? Eating fat can improve my cholesterol? Sounds crazy, right? That goes against everything we have heard from the medical establishment. Notice I said “cholesterol.” I didn’t say the “bad” low density lipoprotein (LDL), I didn’t say the “good” high density lipoprotein (HDL), or any one specific type of cholesterol. We have over emphasized the solitary variable of LDL for too long. Total cholesterol to HDL ratio, Triglyceride to HDL ratio, lipoprotein size and density, insulin sensitivity, and other metabolic measures are more powerful predictors of cardiovascular health than just LDL.Once again, we see that all these markers improve with a Low Carb High Fat (LCHF) lifestyle. The medical establishment needs to realize that we are more complicated than one lab value. The key is to look at the whole picture, and this picture dramatically improves with a LCHF lifestyle.If you want to learn more about lipids and cholesterol, I recommend checking out my new dedicated cholesterol course: The Truth About Lipids. - Higher HDL is Associated with a Lower Risk of Heart Disease.
HDL is your friend, but drugs are not. Observational evidence has consistently shown that higher HDL is associated with a lower risk of cardiovascular disease. However, our healthcare establishment does not prioritize HDL for one simple reason- Drugs that raise HDL don’t make you healthier. Trial after trial has failed to show any benefit from drugs that significantly increase HDL.Instead, it’s the HDL-raising lifestyle that provides the benefit, not artificially increasing it with drugs. What’s the best lifestyle to naturally raise HDL? You guessed it. LCHF/Keto lifestyle. Add in some resistance training and you have your friendly HDL climbing the way it was meant to…Naturally. - LCHF Leaves You Feeling Great, Leading to Healthier Decisions
What kind of health decisions do you make when you are fatigued, achy, and find it difficult to concentrate? That’s a rhetorical question, I already know the answer. When things look glum and we don’t feel well, it’s far too easy to sit on the couch or reach for the chips and cookies. Compare those decisions to those you make when you are well rested, energetic, and seeing the world more clearly. For most people, the better you feel, the better decisions you make.Guess what? The majority of people who change to a LCHF lifestyle feel better! It may take a few days or weeks, but in general, they feel more in control of their health, more energetic, and they are able to make better health decisions. I admit this is difficult to prove in a scientific trial. That is why we all should become our own n=1 scientific trial. How do you feel and how are your health decisions after going to a LCHF lifestyle? What matters most is what works for you, not what works for hundreds of people who are kinda-sorta like you. - Keto helps you with fasting.
Eating better helps you not eat. People who eat a high carb diet eat a lot, don’t they? They are always grazing and snacking. Our bodies go through the roller coaster of blood sugar and insulin spikes, making it a challenge to go 24, 18, or even 6 hours without eating. This creates a constant, unwavering supply of insulin in our blood stream.Why is this harmful? For one, it promotes fat storage and keeps us from using our fat as fuel. Secondly, chronically elevated insulin can predispose to heart disease, strokes, cancer, dementia and other devastating health conditions. When people change to Keto, however, they realize they do not need to eat nearly as much or as frequently. Avoiding the carbs and increasing the fats keeps us full longer, and our bodies quickly adapt to longer periods without eating. The result? We can use our fat stores for what they were designed- a source of fuel! It also allows our body to maintain lower insulin levels, and also allows our cells to take care of their health chores, referred to as Autophagy.If you’re interested in Fasting and want to make sure you’re doing it correctly, download my free Full Guide to Fasting. - LCHF Promotes Health Through Increased Autophagy.
Autopha-What? In medicine we like using fancy words to make us look smart. Autophagy is a big word to describe cellular housekeeping. When we have low enough intake of carbs and protein, or when we do intermittent fasts, our bodies can take care of their “to do” lists. That list includes breaking down weak or damaged cells, recycling the good parts and discarding the rest, and slowing down the processes that can lead to abnormal cell growth (i.e. excess proteins in Alzheimer’s disease, abnormal cancer cells etc.).Admittedly, long term outcome studies evaluating fasting or LCHF and cancer or dementia risk have not been done. But, on the flip side, drug trials to prevent the same are showing no benefit despite hundreds of millions of dollars invested. If you asked me (which you sort of did since you are reading my article), I’d vote for autophagy as a preventative strategy any day. It makes good physiologic sense, and it is so easy to achieve. - With Keto You Will Enjoy Eating Again!
That’s right. A way of eating that helps you lose weight, helps you feel better, improves your health and is actually enjoyable! No fake processed soy products, no cardboard tasting rice cakes. True, it also means no more candy, processed snack foods, doughnuts and danishes. But once you swear them off for a few weeks, and you are eating all the eggs, avocados, nuts, fish, steak, cheese etc. that you want, you won’t miss those old crutches any more. Let the enjoyment begin!
I could go on, but since it seems people like “7 Reason” articles, I will leave it at that.
Now you know the secret: Look at the whole picture. Look for a lifestyle, (not a diet) that helps you feel better, increases your enjoyment, and still benefits your overall health.
Is LCHF/Keto the right lifestyle for you? It just may be. To learn more about Low Carb and Keto, download this free E-Book:
Thanks for reading,
Bret Scher, MD FACC
Founder, Boundless Health
www.LowCarbCardiologist.com
ADDENDUM!!
Since I have published this article, there has been a windfall of media buzz around low carb diets increasing our risk of heart disease or diabetes. Let’s look at where that information came from.
1- A study force feeding mice excessive amounts of industrial omega 6 oils. You can guess what I have to say about that. The article was incredibly helpful, and I immediately stopped force feeding my pet mice industrial seed oils. Thanks goodness for that article. As for how it applies to humans eating real food that contain fat, there is zero correlation.
2- Epidemiological study suggesting those who ate low carb (40% calories from carbs, which by the way is NOT low carb) as measured by two food journals over 25 years had a higher risk of dying. Oh and by the way, at baseline they were heavier, more sedentary, smoked more, and ate fewer veggies. Yet somehow they concluded it must be the low carb diet that “caused” the harm. Once again, it may not be bad science, but it sure was awful interpretation of the science.
In light of those two studies and the hoopla surrounding them, has anything happened to change my mind about a LCHF/keto diet being beneficial for our overall health and our heart health?
Absolutely not.
We still need to individualize our care and our lifestyle for who we are and how our bodies respond. That is always the case regardless of our nutrition, our medications, our exercise etc. As long as we do that, then this cardiologist still believes that LCHF IS HEART HEALTHY!
If you liked this post, you’ll love my free E-Book on Low Carb/Keto Starter tips to help you get started on your LCHF path!
Thanks for reading.
What Does My Cholesterol Level Mean?
Depending on how you look at it, cholesterol can be an incredibly simple topic, or an incredibly confusing one. Contemporary medicine teaches that cholesterol is “bad” and should be low. That seems pretty simple, right? Get it tested, if it’s high, start a drug to lower it.
Times have changed. Now, cholesterol is much more complex, and we all need to be armed with knowledge before we sit down with our doctors to evaluate our cholesterol levels.
Here is my guide to you and your doctor for evaluating your cholesterol.
1. Understand the difference between Total Cholesterol (TC) and high density lipoprotein (HDL) and low density lipoprotein (LDL)
If you doctor is referring to your total cholesterol (TC) and is making decision based on your TC— Run, don’t walk. Run away and find another doctor. TC is comprised of low density lipoprotein (LDL), so-called “bad cholesterol” even though it isn’t bad. High density lipoprotein (HDL), so-called “good cholesterol”, and remnant cholesterol (VLDL and IDL). Initial studies in the 1960s and 70s looked at TC and risk of cardiovascular disease (CVD) and found a weak association. That was prior to when scientists learned how to measure LDL and HDL.
Studies then looked at the individual lipoproteins (i.e. LDL and HDL) and found the higher the LDL, in general, the higher the risk for CVD. And the higher the HDL< the lower the risk of CVD. So, while talking about TC was cutting edge in the 60s and 70s, it is woefully outdated today. That is why if your doctor is still evaluating and treating TC—Run!
2. Does Your Doctor Know Your TC to HDL and TG to HDL Ratios?
If your doctor does not know your ratios, this is another reason to run away and find another doctor (We are doing lots of running here, bonus exercise!) Studies in the early 2000s and more recently have shown that total cholesterol to HDL ratio (TC:HDL) and triglyceride to HDL ratio (TG:HDL) are BETTER predictors of cardiovascular risk than isolated LDL, TC or HDL.
By incorporating TG and HDL into the analysis, these ratios incorporate the impact of remnant cholesterol and track with insulin resistance, both strong predictors of CVD. These ratios are calculated from a standard lipid profile, so they do not require any special testing or special labs. They are widely available for everyone to see. So if your doctor is not using them to evaluate your lipids, it’s time to find a new one.
3. Understanding a Familial hypercholesterolemia (FH) diagnosis
Familial hypercholesterolemia (FH) is a diagnosis that requires (wait for it…) a family history! As the name suggests, it is an inherited condition passed from generation to generation. All too often, doctors will see an LDL level over 190 and make the diagnosis of FH. If your doctor makes that diagnosis that based on level alone without a family history, run!
There is a well-accepted scoring system, The Simon Broome Criteria, to help determine if someone has FH. This equation factors in age of diagnosis, absolute level of LDL, in addition to family history of early onset hyperlipidemia or early onset heart disease. It makes a big difference if you have FH or not. Don’t let your doctor label you as having FH without applying the full criteria. Just wait for the look on their face when you respond, “What was my Broome score? Did it confirm I have FH?” and hope you don’t hear crickets.
4. What is Advance Lipid Testing?
Advance lipid testing may be helpful. And it may not. Advanced lipid testing can tell us the size, density, and inflammatory characteristics of our lipoproteins. This can help further risk stratify the potential danger of our lipids. For instance, small, dense LDL tend to correlate more strongly with CVD, whereas so-called pattern A LDL (the larger, less dense version) does not correlate as well.
Here is the interesting part. Those with high TG and low HDL almost uniformly have small dense LDL and increased inflammation. Conversely, those with low TGs and high HDL have Pattern A, larger less dense LDL. Are you starting to see a pattern? Low TG and high HDL=good. High TG and low HDL=bad.
Sometimes, however, there can be variation in this equation. Therefore, I usually suggest people get advanced lipid testing one time to see if their results correlate. If they do, then you can just follow your ratios to predict your advanced results. Why not get them all the time? They are frequently not covered by insurance and can be expensive.
5. Interpret your lipids in context
Lipids don’t exist in a vacuum. They exist in your body, so it’s important to take into account what else is going on in your body. Insulin resistance and inflammation can directly affect your lipids and increase your risk in general. Hypertension, obesity, and family history of heart disease also play crucial roles in determining your risk.
Therefore, if your doctor checks only your lipids and bases decision on those labs alone—Run! Instead, you should get a hsCRP, Hgb A1c, fasting glucose, insulin and HOMA-IR, BP measurement, family history assessment, and complete history. This is the context in which your lipids should be evaluated. Not alone in a vacuum.
6. Why test a risk factor that may be related to CVD risk when you can test the disease itself?
Good question, right? To truly know what your lipids mean to you, you also need to know if you have evidence of CVD. Coronary artery calcium scores and Carotid Intima Media Thickness (CIMT) are two easy, relatively inexpensive tests, that you can get to show you whether or not you have current evidence of CVD. The presence or absence of disease significantly impacts the risk of lipid levels.
So, What Does Your Cholesterol mean to You? It depends.
It depends on many factors, and only by evaluating ALL of those factors can you truly know what impact your lipids may be having on our health. Anything short of this evaluation is an inadequate and antiquated approach to lipids.
Now you are forewarned and forearmed, and you can walk into your doctor’s office ready to ask the important questions and help guide the workup so that you can know what your cholesterol means to you.
Thanks for reading, and as always, please let us know If you have any comments or questions.
Bret Scher MD FACC
Founder, Boundless Health
www.LowCarbCardiologist.com

Do we have to avoid meat if we have high homocysteine levels? Not really.
What our body does with homocysteine is more important than our food intake. I thought this was easier to explain in video form, so you can see my 4 minute explanation here:
The bottom line is we need to know our methylation status, make sure we have adequate levels of folate, B12 and B6, and make sure we have adequate choline (found in egg yolks). If all those are perfect, and we still have elevated homocysteine, then we may want to experiment with a diet low in methionine to see if it makes a difference.
As always, however, we have to evaluate our overall health picture and not get too hung up on one blood marker. The more important questions to ask are how does homocysteine affect my overall health, and how will altering my supplements or diet change the big picture?
Hopefully this helps! Let me know if you have any comments or questions.
Thanks for reading (and watching!)
Bret Scher MD FACC

Here it is again. The term “healthy” connected as a descriptor.
We see it all the time. Healthy Whole Grains. It reminds me of the common use of “fruits and vegetables,” as if they are one in the same.
Are whole grains, by definition, “healthy?”
For a full, in depth description, see the Whole Grains Guide on Diet Doctor, where I was the medical editor and reviewer.
For the quick answer, let’s leave it as a “maybe.”
If you choose to eat refined grains, white flour, processed snack foods, in essence the Standard American Diet, then switching to whole grains will almost certainly improve your health. And that is where the majority evidence in favor of whole grains stops. Compared to refined grains, they are great.
Who should eat whole grains?
If you are insulin sensitive, live in a society where you are physically active for most the day, eat fewer calories than most industrialized nations, and maintain a healthy body weight, then whole grains can be a healthy part of your diet. Observation of the Blue Zone countries demonstrate that whole grains can be part of a healthy lifestyle in that setting.
We cannot, however, extrapolate those findings above to apply to all Americans, Europeans, Asians etc. and say whole grains are by definition “healthy.”
Who should not eat whole grains?
If you are metabolically unhealthy with diabetes, metabolic syndrome or insulin resistance (estimated to be 88% of all Americans), then whole grains are anything but “healthy.” Borrow a continuous glucose monitor for a day and see how your blood glucose responds to whole grains. If you aren’t perfectly metabolically healthy, it isn’t pretty.
Instead, if you eat a whole-foods, low carb diet without grains and sugars, then whole grains have no necessary role and no association with health.
Enjoy the more detailed guide from DietDoctor.
Thanks for reading,
Bret Scher, MD FACC
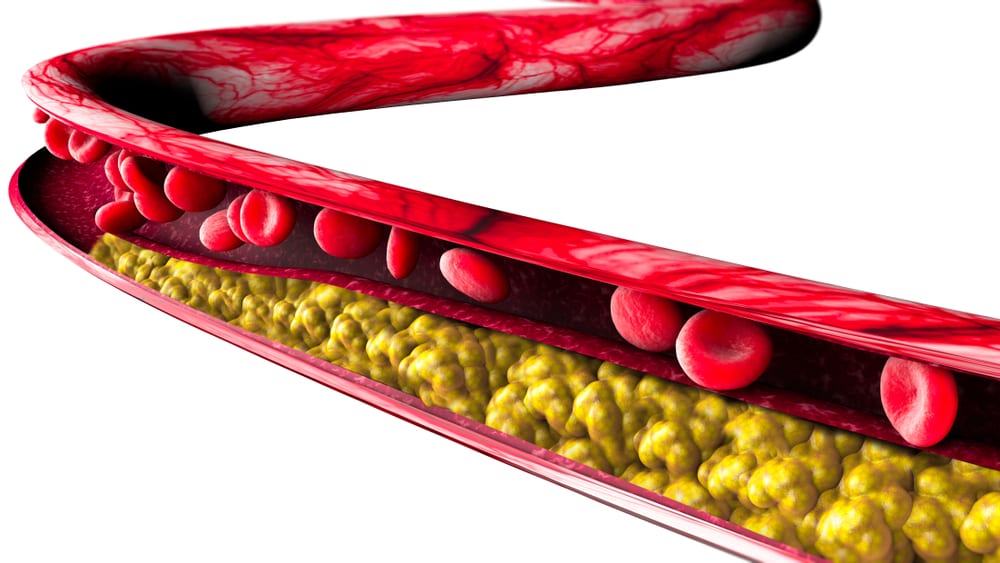
Don’t look now, but the updated clinical practice cholesterol guidelines from the American College of Cardiology, the American Heart Association and others are getting personal. Although the guidelines still contain their familiar approach — that I consider too aggressive with drug therapy — the latest 2018 version of the guidelines now includes an impressive update to emphasize lifestyle intervention, plus a more individualized approach for risk assessment.
MedPage Today: AHA: Revised Lipid Guide Boosts PCSK9s, Coronary Calcium Scans
Could this be the start of a progressive trend away from shotgun statin prescriptions? I sure hope so.
Prior guidelines emphasized the 10-year ASCVD risk calculator as the main determining factor for statin therapy. In the 2018 update, the guidelines acknowledge that the calculator frequently overestimates the risk in those individuals who are more involved with prevention and screening. (In other words, those patients more interested in and proactive about their health; I find many in the low-carb world fall into this category.)
The ensuing discussion with a healthcare provider should then focus on:
[T]he burden and severity of CVD risk factors, control of those other risk factors, the presence of risk-enhancing conditions, adherence to healthy lifestyle recommendations, the potential for ASCVD risk-reduction benefits from statins and antihypertensive drug therapy, and the potential for adverse effects and drug–drug interactions, as well as patient preferences regarding the use of medications for primary prevention… and the countervailing issues of the desire to avoid “medicalization” of preventable conditions and the burden or disutility of taking daily (or more frequent) medications.
I appreciate the attention the new guidelines bring to the depth of the discussion that should ensue between doctor and patient. Considering the treatment burden is equally as important as the burden of disease, and possibly even more important in patients who have not been diagnosed with heart disease, these individualized discussions about trade-offs are critical to personalized care.
Also worthy of mention is the increased use of coronary artery calcium scores (CAC) to help individualize risk stratification. The updated guidelines specify CAC may be useful for those age 40-75 with an intermediate 10-year calculated risk of 7.5%-20%, who after discussion with their physician are unsure about statin therapy. They specify that a CAC of zero would suggest a much lower risk than that calculated by the ASCVD risk formula, and thus take statins off the table as a beneficial treatment option.
This is huge. I cheered when I read this! I have been critical of prior guidelines that focused on ways to find more people to place on statins. The mention of finding individuals unlikely to benefit from statins is a giant step in the right direction.
The guidelines go even further: they mention that a CAC either over 100 or greater than the 75th percentile for age increases the CVD risk and the likely benefit of a statin. A CAC between 1-99 and less than the 75th percentile does not affect the risk calculation much and it may be worth following the CAC in five years in the absence of drug therapy. I would still argue that a CAC >100 does not automatically equal a statin prescription and we need to interpret it in context, but I greatly appreciate this attempt at a more personalized approach.
The guidelines also go beyond the limited risk factors included in the ASCVD calculator by introducing “risk modifying factors” such as:
- Premature family history of CVD
- Metabolic syndrome
- Chronic kidney disease
- Chronic inflammatory conditions such as rheumatoid arthritis and psoriasis
- Elevated CRP > 2.0 mg/L
- Elevated Lp(a) > 50 mg/dL or 125 nmol/L
- Elevated triglycerides > 175 mg/dL
Although they use these criteria to define an increased risk, the opposite would likely hold true. An absence of those criteria could define a lower risk situation.
Some changes deserve mention from a controversy standpoint as well. For instance, the new guidelines recommend checking lipid levels as early as two years old in some circumstances. Two!
They also recommend statin therapy for just about everyone with diabetes with no mention of attempting to reverse diabetes before starting a statin, a drug that has been shown to worsen diabetes and insulin resistance. In addition, the new guidelines do not mention the likely discordance between LDL-C and LDL-P in those with diabetes.
Last, the new guidelines define an LDL-C > 190 mg/dL as an absolute indication for statin therapy with a treatment goal of 190 mg/dL is in familial hypercholesterolemia populations (and even then has heterogenous outcomes). There is a clear lack of data supporting that same recommendation for metabolically healthy individuals with no other cardiac risk factors and no other characteristics of familial hypercholesterolemia. This is a clear example of when a guideline turns from “evidence based” to “opinion based.”
In summary, the guideline committee deserves recognition for its emphasis on an individualized care approach, its use of CAC, and its broader description of discussing potential drawbacks of drug treatment. It still combines opinion with evidence and believes all elevated LDL is concerning, but I for one hope it will continue its progression away from generalizations and someday soon see that individual risk variations exist, even at elevated LDL-C levels.
Thanks for reading,
Bret Scher MD FACC
Originally Posted on the Diet Doctor Blog
TAKING YOUR NEXT STEP
WITH BOUNDLESS HEALTH AND DR. SCHER
We are excited to help you in your quest for better health! If you are ready to take the next step, your annual membership will give you access to:
START A CONVERSATION
Connect with Dr. Scher to see if this model is right for you today.
Let’s Talk
Send us a message and let us know how we can help you.